OpenEvidence vs ChatGPT: Which Should Doctors Use?
OpenEvidence vs ChatGPT for doctors: a physician compares clinical accuracy, medical citations, safety evidence, and the best use for each AI tool.
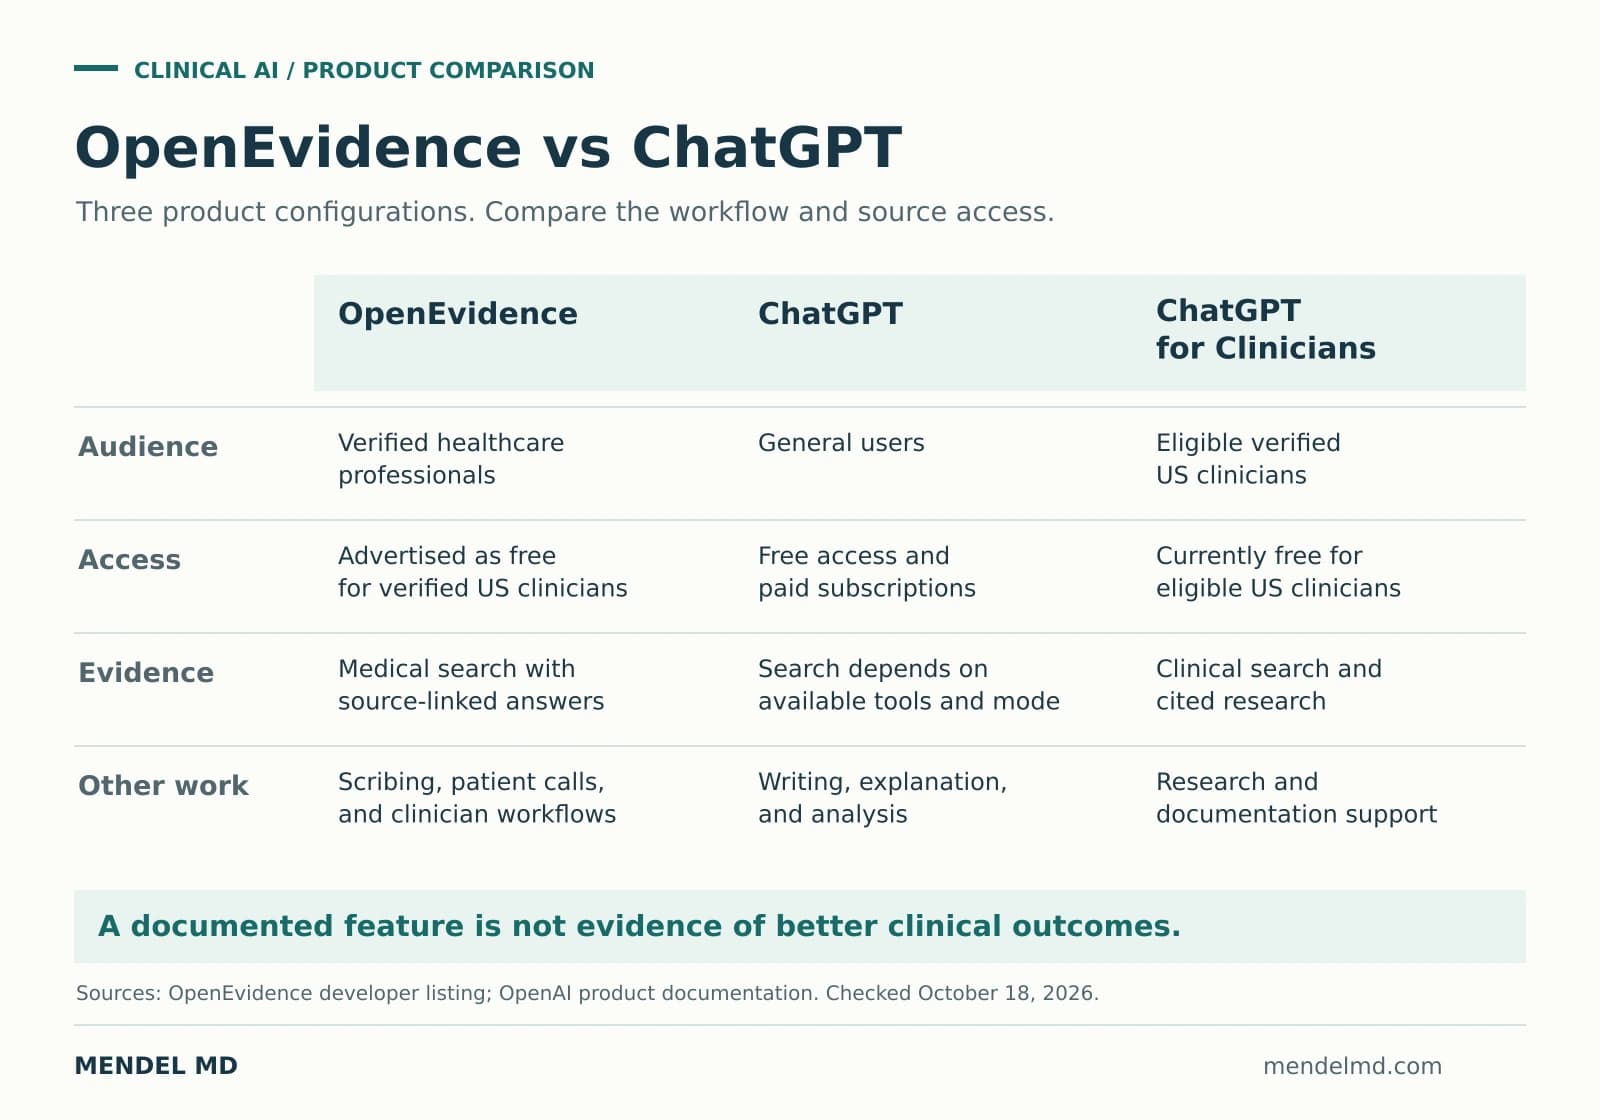
The short answer. For a focused clinical question, OpenEvidence is often my first stop because it gets me into the medical literature quickly and shows me sources I can inspect. Ordinary ChatGPT is more flexible for explanation, drafting, and exploring a problem from different angles. ChatGPT for Clinicians narrows that gap by adding clinical search, citations, and medical workflows.
There is still no universal winner. In current studies, frontier general-purpose models performed better on selected knowledge and response-quality benchmarks, while OpenEvidence performed better on particular citation audits. Safety-focused studies also suggest advantages for specialized clinical tools on some tasks. None of that proves that one product improves patient outcomes across routine care.
That is the practical answer. The rest of this article explains why the evidence is more complicated than the product comparison makes it look.
Disclosure: I use OpenEvidence regularly, including when researching my writing. I have no financial relationship with OpenEvidence, OpenAI, or the other companies discussed. Product details and evidence are current through October 18, 2026.
Why this comparison matters now
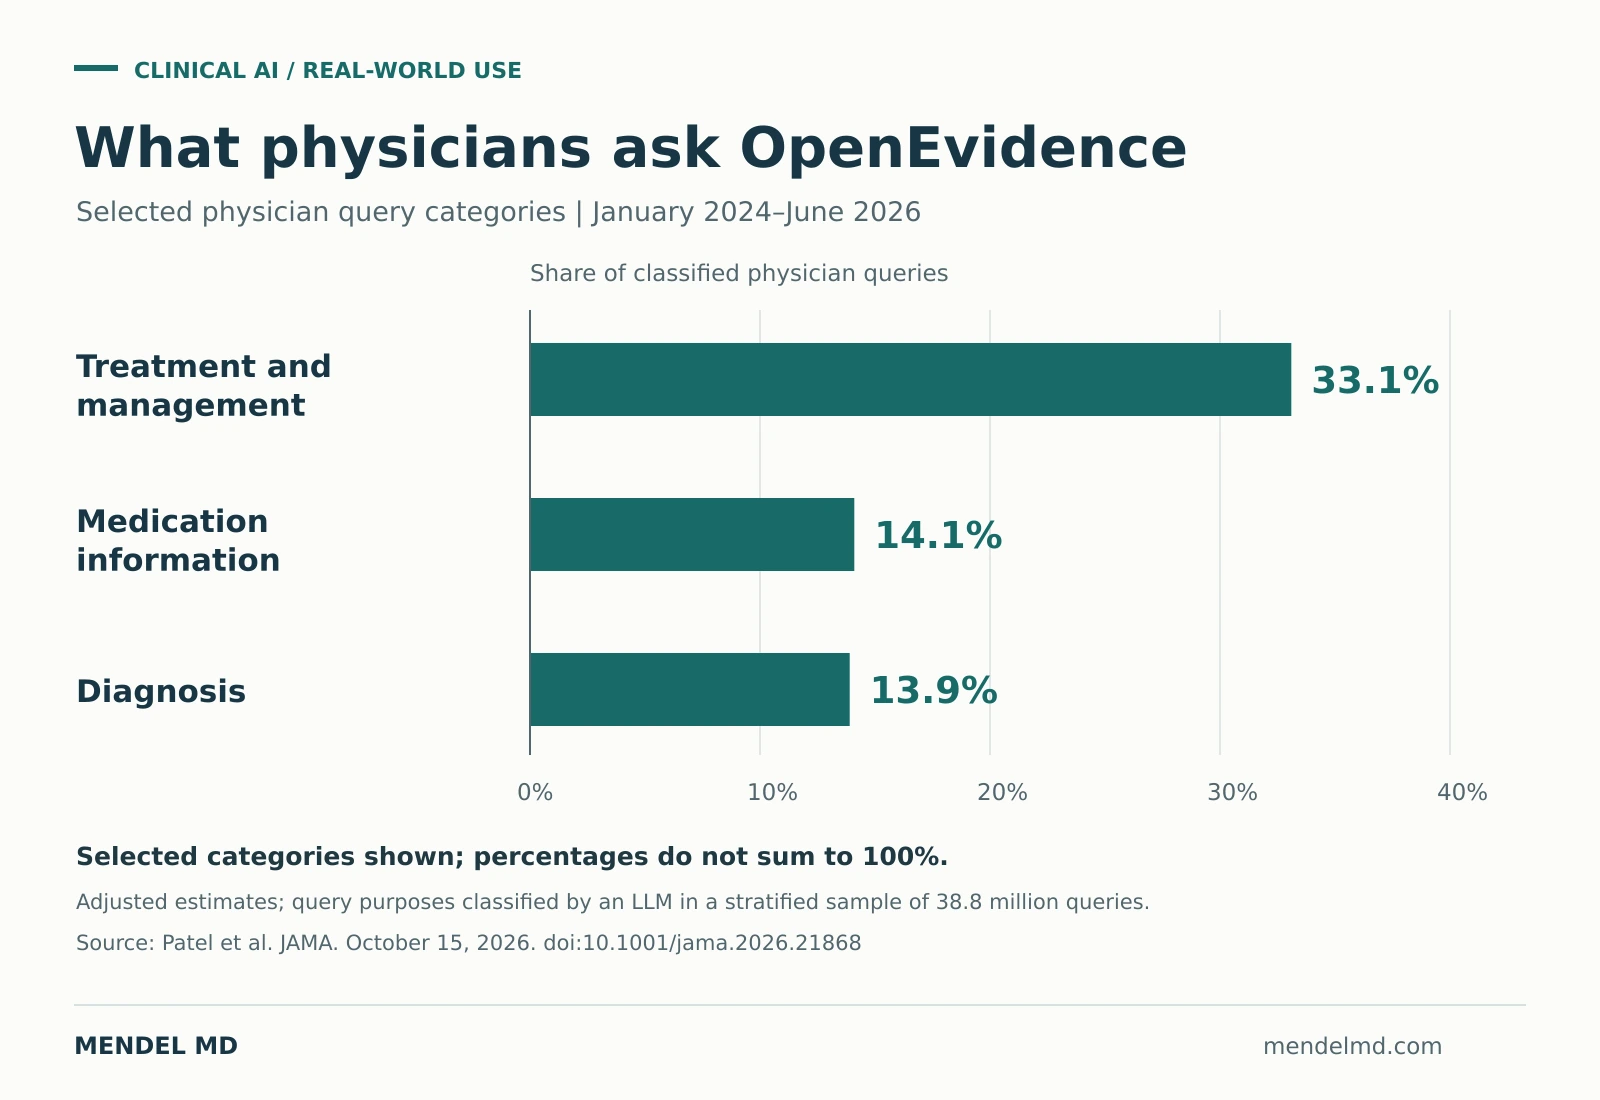
OpenEvidence is no longer a niche experiment. A JAMA study published October 15, 2026, analyzed 271 million queries submitted by 952,008 US clinicians over two and a half years.[1] Monthly active users increased from 355 in January 2024 to 703,265 in June 2026, and monthly queries per active user rose from 18.0 to 39.5.
The pattern of use matters as much as the scale. Physicians were most often asking about treatment and management, not diagnosis. That is a harder and more consequential job than answering a board-style question: the tool has to find relevant evidence, interpret it correctly, identify important exceptions, and fit the answer to a real clinical decision.
The study also deserves context. It analyzed one platform's own logs, could not determine whether the questions were asked during patient care or changed management, and included three authors affiliated with OpenEvidence. It tells us that clinicians are using the product repeatedly. It does not tell us that the answers improved care.
Early-career physicians were especially heavy users. Physicians within 10 years of graduation represented 24.3% of the workforce but generated 61.8% of physician queries.[1] As an early-career physician, I understand the appeal. Medicine repeatedly asks you to move from knowing about a disease to deciding what to do next, often outside the narrowest part of your training.
That is also why the evaluation has to match the real use. A high exam score is interesting. It is not enough if physicians are asking for management guidance.
OpenEvidence vs ChatGPT: what are we actually comparing?
The word “ChatGPT” now describes more than one product context.
OpenEvidence is an AI-enabled clinical information platform for verified healthcare professionals. It synthesizes answers to free-text medical questions and provides inline citations to medical literature and guidelines.[1][13]
Ordinary ChatGPT is a general-purpose product. Its medical usefulness depends on the model, plan, available search tools, and the way the question is asked.
ChatGPT for Clinicians is a separate workspace for eligible verified US clinicians. OpenAI describes it as including clinical search with citations, medical deep research, documentation support, and clinician-specific workflows.[2] It is currently free for eligible verified US clinicians, although access rules can change.
- OpenEvidence: Best suited to focused clinical questions and fast evidence retrieval. Its main advantage is medical search with source-linked answers. Its main limitation is that a real citation can still be misinterpreted or incompletely applied.
- ChatGPT: Best suited to explanation, drafting, analysis, and broad problem-solving. Its flexibility is the advantage; its results depend heavily on the model and enabled tools.
- ChatGPT for Clinicians: Best suited to clinical search, cited research, and documentation workflows. It combines ChatGPT's interface with clinician-focused retrieval, but it is a newer product and studies of older ChatGPT versions do not directly evaluate it.
The most important point is that these products change. A study of ChatGPT-4o in 2025 is not a direct test of a later model or of ChatGPT for Clinicians. The same applies to OpenEvidence. A useful comparison should always name the version, date, task, and outcome.
If you want a deeper look at OpenEvidence by itself, I have a separate physician review of OpenEvidence. For the broader methodology, see how I evaluate clinical AI across five layers.
Is OpenEvidence more accurate than ChatGPT?
It depends on what “accurate” means.
A board-style question, a clinician-rated response, a citation audit, a harmful-omission test, and a trial of physician use measure different things. The studies only look contradictory when those outcomes are collapsed into one score.
On medical knowledge and answer quality, frontier models led one major comparison
A 2026 Nature Medicine study compared OpenEvidence and UpToDate Expert AI with GPT-5.2, Gemini 3.1 Pro Preview, and Claude Opus 4.6. The evaluation included 500 MedQA questions, 500 HealthBench items, and 100 real clinician queries.[3]
On MedQA, GPT-5.2 scored 94.2% and OpenEvidence scored 89.6%. Frontier models also led on HealthBench and on clinician ratings of the 100 real queries.
That result challenges the assumption that a specialized medical product must outperform a general-purpose frontier model. It does not settle the comparison. The study did not assess citation quality or latency, the products were accessed on different dates, and the authors acknowledged possible benchmark contamination and evaluator affinity. A later critique and author reply debated how broadly the findings should be generalized.[4][5]
This is exactly why I separate medical knowledge benchmarks from clinical usefulness. A model can answer more test questions correctly and still be less convenient for finding the paper you need.
On citation fidelity, OpenEvidence led a specialty comparison
A cervical-spine guideline study asked 110 questions of OpenEvidence 2.0 and ChatGPT-4o in June and July 2025.[6] All 999 OpenEvidence citations met the study's accuracy criteria, compared with 184 of 393 ChatGPT citations, or 46.8%. Guideline alignment also favored OpenEvidence.
That is a meaningful result for the tested task. It does not prove that every OpenEvidence answer is correct, that every citation supports every nearby sentence, or that the same gap exists between current products.
On potential harm, omissions may matter more than obvious errors
The July 2026 NOHARM preprint evaluated 1,100 simulated clinical consultation tasks and reported lower potential harm for the specialized clinical tools it tested than for generalist models.[7] More than 80% of severe errors were omissions.
That finding changes what I look for. The dangerous answer is not always the one containing an absurd recommendation. It may be the polished answer that leaves out the contraindication, escalation step, follow-up test, or alternative diagnosis that mattered most.
NOHARM is a preprint and used simulated assessments, not observed patient injuries. It supports checking completeness separately from correctness; it is not a universal safety certification.
Can you trust medical AI citations?
A citation can fail in two different ways.
- The source is fabricated or irrelevant. The link or paper does not exist, or it has little to do with the claim.
- The source is real, but the conclusion is overstated. The paper exists and sounds relevant, yet it does not support the exact statement attached to it.
The second failure is harder to catch because the source trail looks legitimate.
SourceCheckup, published in Nature Communications in 2025, evaluated whether cited medical sources actually supported generated claims.[8] For GPT-4o with web search, about 30% of individual statements were unsupported, and nearly half of complete responses were not fully supported. Those findings came from an older configuration, but the underlying lesson still applies: retrieval makes a claim checkable; it does not make the interpretation correct.
A cardiology example: lipoprotein(a) and the FOURIER analysis
Imagine asking what elevated lipoprotein(a), or Lp(a), means when LDL cholesterol is already low. An answer might cite the FOURIER analysis of Lp(a) and evolocumab. That study included 25,096 participants with established atherosclerotic cardiovascular disease. Higher Lp(a) was associated with coronary risk independent of LDL cholesterol, and evolocumab reduced Lp(a) by a median of 26.9% at 48 weeks.[9]
Now imagine the answer concludes: “This proves that lowering Lp(a) with a PCSK9 inhibitor benefits any patient with elevated Lp(a).” That sentence is a hypothetical overstatement I created for illustration, not an output collected from either product.
The citation is relevant, but the conclusion travels too far. The study population had established cardiovascular disease. Evolocumab changes more than one lipid measure. The analysis cannot isolate the benefit of lowering Lp(a) alone or support a universal treatment recommendation.
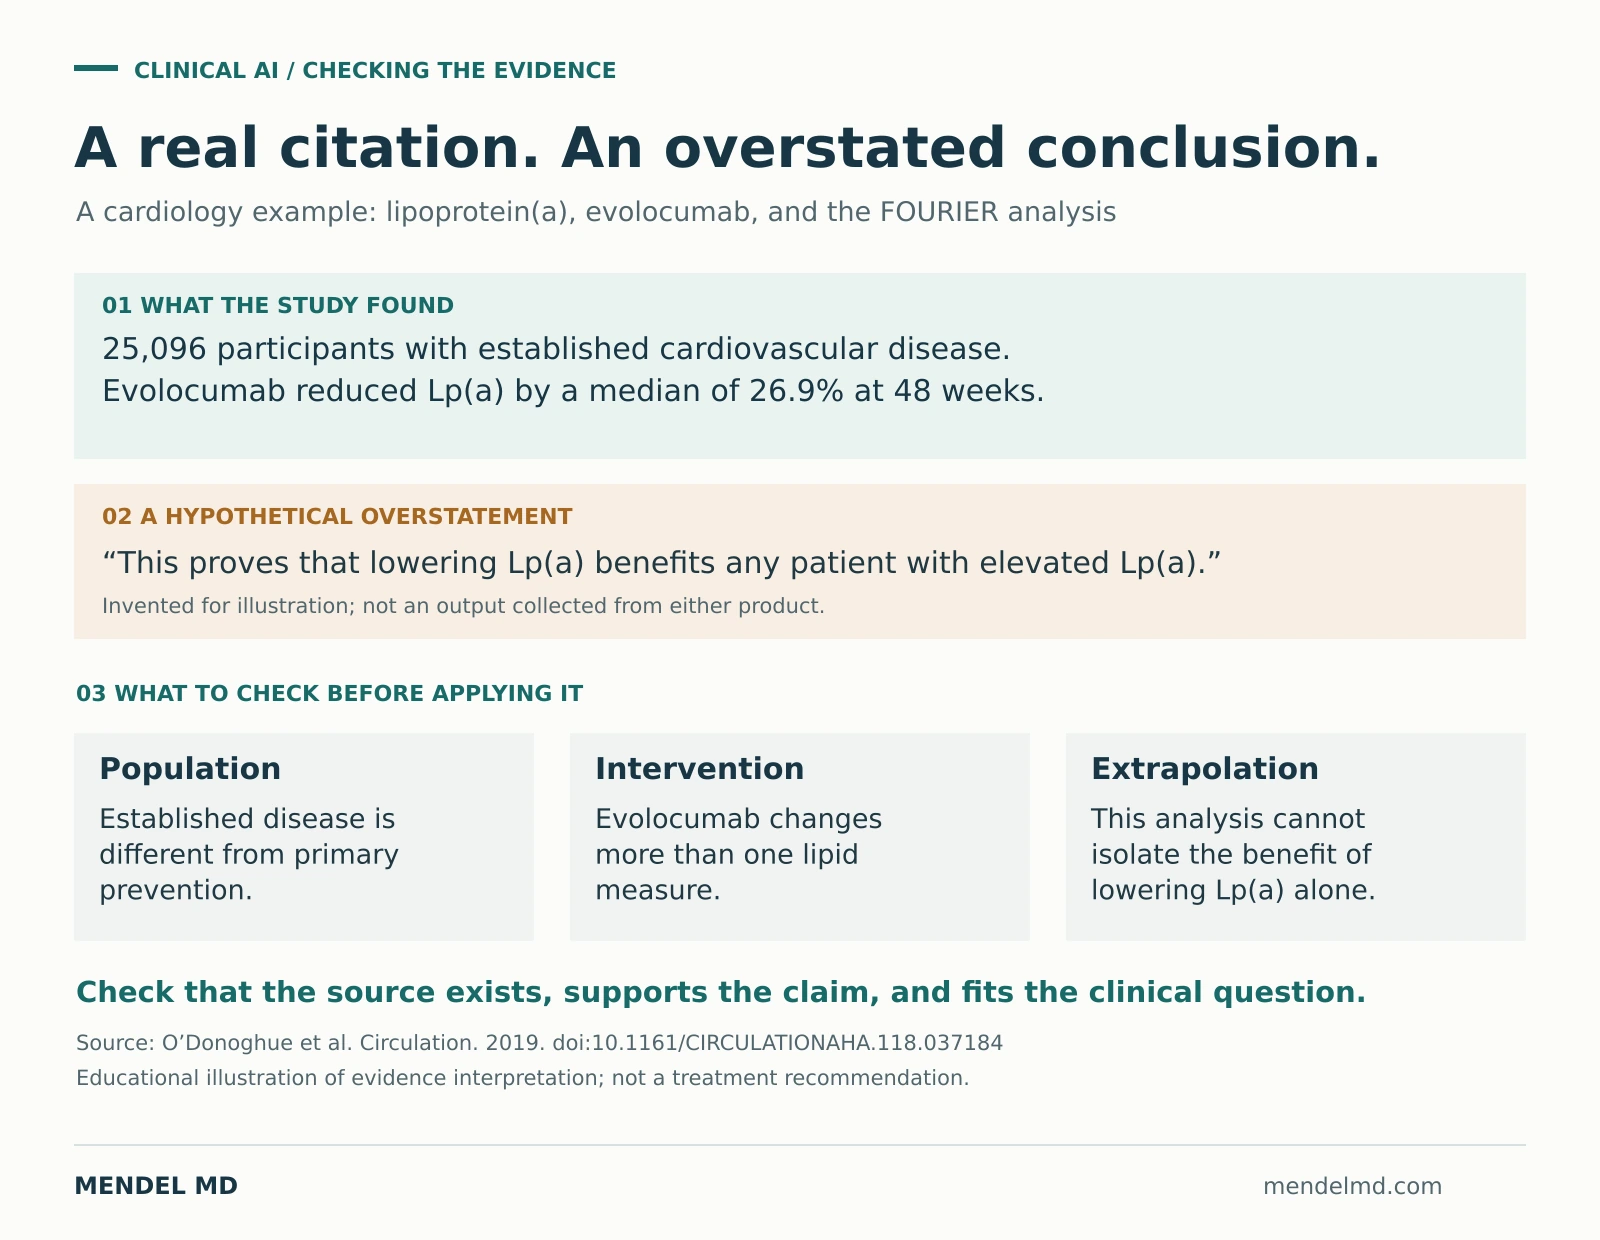
This is the kind of verification I want an AI tool to make easier: show what the study demonstrates, where extrapolation begins, and which missing facts could change the decision. The citation gives me a route to that judgment. It does not complete it.
For more background, read my plain-English guide to lipoprotein(a) or use the Lp(a) risk calculator to place a laboratory result in context.
Does AI help doctors make better decisions?
This is the more important question, and the evidence is thinner.
In a randomized diagnostic-reasoning study of 50 physicians, access to GPT-4 plus conventional resources produced a median score of 76%, compared with 74% for conventional resources alone.[10] The adjusted difference was 2 percentage points, with a 95% confidence interval from −4 to 8, and was not statistically significant.
A separate randomized trial of 92 physicians evaluated management reasoning rather than diagnosis. GPT-4 assistance improved performance by 6.5 percentage points, but physicians also spent about two additional minutes per case.[11]
Those results are not inconsistent. They tested different tasks. They also show why workflow matters: giving a physician access to a capable model does not guarantee that the physician will use it effectively.
Patient outcomes require a different kind of study. A pragmatic cluster-randomized trial across 16 primary-care facilities in Kenya enrolled 9,691 patients.[12] Fourteen-day treatment failure was 2.2% with LLM assistance and 2.0% with usual care. The adjusted odds ratio was 0.77, with a 95% confidence interval from 0.55 to 1.08, so the difference was not statistically significant.
That was one specific workflow and not a head-to-head trial of OpenEvidence and ChatGPT. It is still a useful reminder: impressive answers and benchmark scores do not automatically become better patient outcomes.
Which should doctors use?
My own workflow is simple.
For a focused clinical question, I usually start with OpenEvidence
If I am asking about a treatment threshold, drug interaction, trial, or guideline recommendation, I want a short route into the literature. OpenEvidence is useful because it puts the synthesis and sources together.
I still open any citation supporting a claim that could change management. I check the study population, intervention, comparison, outcome, date, and whether a newer guideline changes the context.
For explanation, drafting, or another angle, I use ChatGPT
ChatGPT is useful when I want help structuring an explanation, comparing interpretations, drafting patient-facing language, or identifying questions I may have missed. ChatGPT for Clinicians may also support source-linked clinical work, but evidence about prior consumer ChatGPT configurations should not be treated as a direct evaluation of that newer workspace.
One follow-up I find useful is:
What information could change this answer, and which conclusions require extrapolation?
That question does not make the output true. It does often expose a missing contraindication, a population mismatch, or a place where the model sounded more certain than the evidence allowed.
For an actual decision, I use the appropriate clinical system
Neither product replaces local policy, a current guideline, the patient record, a pharmacist, or specialist judgment. The right source depends on the decision. A hospital protocol may matter more than a literature synthesis. A subspecialist may recognize a context that no retrieval system captured.
I also avoid treating agreement between two chatbots as independent confirmation. They may share sources, training patterns, or the same blind spot.
A practical checklist before using either answer
- Name the task. Are you asking for facts, evidence retrieval, explanation, diagnosis, management, or documentation?
- Check the version and date. Product behavior can change faster than the literature evaluating it.
- Open the decisive citations. Verify that each source exists and supports the attached claim.
- Check applicability. Compare the study population, intervention, setting, and outcomes with the patient in front of you.
- Look for omissions. Ask what important test, contraindication, escalation step, or alternative may be missing.
- Use local guidance. Institutional policy and current specialty guidelines can supersede a general synthesis.
- Keep professional judgment in the loop. The clinician remains responsible for the decision.
Frequently asked questions
Is OpenEvidence better than ChatGPT for medical questions?
OpenEvidence is often the more direct tool for focused evidence retrieval. ChatGPT is more flexible for explanation, drafting, and broad problem-solving. Research has favored different products on different outcomes, so there is no universal winner.
Is OpenEvidence more accurate than ChatGPT?
Not across every measure. One 2026 comparison favored frontier general-purpose models on medical knowledge and clinician-rated answers, while a specialty study favored OpenEvidence on citation accuracy. The tested version, task, and outcome matter.
How does ChatGPT for Clinicians compare with OpenEvidence?
Both support source-linked clinical work. ChatGPT for Clinicians adds clinical search, cited research, and documentation tools to a dedicated clinician workspace. Independent head-to-head evidence on the current products remains limited.
Can OpenEvidence hallucinate?
Yes. Favorable citation results do not guarantee that every answer is correct, complete, or faithfully supported. A real reference can still be applied to the wrong population or used to support a conclusion the study did not establish.
Can ChatGPT provide reliable medical references?
It can provide inspectable references when retrieval is enabled. You still need to confirm that the sources exist, are current, and support the specific claims made.
Are OpenEvidence and ChatGPT for Clinicians free for doctors?
OpenEvidence and ChatGPT for Clinicians currently advertise free access for eligible verified US clinicians.[2][13] Eligibility, limits, and product terms can change.
Does either replace UpToDate or a specialist?
No. AI retrieval, curated expert guidance, local protocols, and specialist judgment solve overlapping but different problems. Choose the resource based on the clinical question and the consequence of getting it wrong.
My two cents
I like OpenEvidence. Its combination of medical search, readable synthesis, and accessible citations solves a real problem for physicians. The new JAMA data suggest I am far from alone.
I also think the strongest general-purpose models are too capable to dismiss as “nonmedical,” especially as clinician-specific products add retrieval and cited research. Product category alone does not tell you which answer will be better.
The useful distinction is more practical: What job am I asking the tool to do, and what evidence would tell me it did that job well? If the job is finding clinical literature quickly, source access matters. If the job is explanation, flexibility matters. If the job is changing care, benchmark scores are not enough.
I want tools that make the work faster without making uncertainty invisible. That means opening the paper, checking what was left out, and remembering that a polished answer is still only the beginning of the clinical judgment.
Subscribe to MendelMD for my writing on clinical AI, preventive cardiology, and building useful healthcare tools.
- How to Evaluate a Clinical AI Tool: The Five Layers
- How Medical AI Got Graded: The Evolution of Clinical LLM Benchmarks
- What Is OpenEvidence? A Physician's Review
- The AI in Healthcare Map
Educational content for clinicians. Not medical advice. Product features and eligibility can change; details checked October 18, 2026.
References
- Patel VR, Finlayson SG, Liu-Hass M, et al. Clinician Use of an Artificial Intelligence–Enabled Clinical Information Platform. JAMA. Published online October 15, 2026. doi:10.1001/jama.2026.21868.
- OpenAI. ChatGPT for Clinicians. Product documentation. Accessed October 18, 2026.
- Vishwanath K, et al. General-purpose large language models outperform specialized clinical AI tools on medical benchmarks. Nature Medicine. 2026;32:2405–2409. doi:10.1038/s41591-026-04431-5.
- Beaulieu-Jones B, Nemati S. Limited benchmarks constrain the conclusions of a general-purpose versus clinical AI comparison. Nature Medicine. 2026. doi:10.1038/s41591-026-04638-6.
- Vishwanath K, Aphinyanaphongs Y, Oermann EK. Reply to: Limited benchmarks constrain the conclusions of a general-purpose versus clinical AI comparison. Nature Medicine. 2026. doi:10.1038/s41591-026-04637-7.
- Avrumova F, et al. Evolution of generative artificial intelligence in clinical practice: comparative performance of OpenEvidence 2.0 and ChatGPT-4o. The Spine Journal. Published online August 31, 2026. doi:10.1016/j.spinee.2026.08.002.
- Wu D, et al. First, do NOHARM: a medical safety benchmark and randomized study of physician and AI teaming on clinical consultations. Version 4, July 13, 2026. Preprint; not peer reviewed.
- Wu K, et al. An automated framework for assessing how well LLMs cite relevant medical references. Nature Communications. 2025;16:3615. doi:10.1038/s41467-025-58551-6.
- O'Donoghue ML, et al. Lipoprotein(a), PCSK9 inhibition, and cardiovascular risk. Circulation. 2019. doi:10.1161/CIRCULATIONAHA.118.037184.
- Goh E, et al. Large language model influence on diagnostic reasoning: a randomized clinical trial. JAMA Network Open. 2024;7:e2440969.
- Goh E, et al. GPT-4 assistance for improvement of physician performance on patient care tasks: a randomized controlled trial. Nature Medicine. 2025;31:1233–1238.
- Agweyu A, et al. Generative AI-enabled clinical decision support system in primary care: a pragmatic, cluster-randomized trial. Nature Medicine. 2026;32:3032–3039.
- OpenEvidence Inc. OpenEvidence developer description and version history. Apple App Store. Accessed October 18, 2026.

Mendel Jacobs, MD, MPH
Menachem "Mendel" Jacobs, MD, MPH is an Internal Medicine Resident at Yale School of Medicine pursuing academic cardiology. He publishes under Menachem Jacobs.
Connect on LinkedInRelated Articles
How to Evaluate a Clinical AI Tool: The Five Layers
Medical AI benchmarks contradict each other because they measure different things. A five-layer framework for evaluating clinical LLMs — from board-exam accuracy to patient outcomes — and why the evaluation layer usually decides the winner.
How Medical AI Got Graded: The Evolution of Clinical LLM Benchmarks
From PubMedQA in 2019 to pragmatic patient-outcome trials in 2026 — how medical AI evaluation evolved, what each generation of benchmarks exposed that the last one couldn't see, and what exam scores can and cannot tell us.
AI in Medicine Review: 6 Stories From August-September 2026
A physician's review of six AI in medicine stories: ChatGPT in Epic, FDA outcomes evidence, SkinVision, AI ultrasound, autonomous mammography triage, and oncology RAG summaries.